
I A T R O G E N E S I S
Unintentional Medical Injury and Trauma
M A D


Mandibular Advancement Device
In May 2025, I relayed the history surrounding my
MAD (mandibular advancement device)
to my San Jose dentist and Phoenix oral surgeon.
They were both shocked.
“Oh my God. This is irreparable”, exclaimed my dentist.
“This is what we’re trying to fix now,” I stated.
My oral surgeon was speechless when he learned the name of the dentist
who had treated my alleged “TMJ” in 1978 with this procedure.
He had known him since that time.
EQUILIBRATION
After a regular dental exam (1977), my dentist sent me to an endodontist; he was concerned about the area above my left canine tooth. With a negative report in hand, he decided to adjust my occlusion and started equilibrating (grinding) my left canine tooth. A bolt of lightening shot through my face. This procedure initiated facial pain.
He stopped his procedure immediately and asked
if I had ever undergone sinus surgery.
My positive response elicited a comment
that I have never forgotten:
“Well, you should have told me you had sinus surgery!”
He then referred me to an equilibration specialist
who then proceeded to adjust my bite
by equilibrating (grinding) all of my natural teeth.
This six-week process created even more facial pain.
(Equilibration of the entire bite is never done today)
DENTAL APPLIANCE
My son was in the third grade and I took him to an orthodontist for evaluation of his occlusion. I was sitting in the waiting room and my facial pain became extreme; tears began rolling down my face just as the orthodontist appeared in the waiting room to talk with me.
He asked me what was wrong and
thus heard my ‘dental equilibration’ story.
He then said I had a TMJ problem
and referred me to a colleague who treated TMJ.
I later learned this dentist was ‘new’ to TMJ treatment and he had been to a workshop with Mandibular Advancement Devices – and thus, I became his first patient with the MAD device
which further created even more pain and problems.
He pulled my mandible (lower jaw) into a Class III malocclusion to ‘recapture the TM disc’
(lower jaw pulled in front of the upper teeth).
In order to prevent my jaw from relaxing / dropping back while sleeping (reclining), he bonded a spike on the bottom appliance so that my maxilla (top teeth)
was unable to go back even with my mouth open.
M A D
Seeing a physical therapist three times a week for two months did not help
my orofacial pain which had then triggered my back pain.
I thus returned to my trusted chiropractor who had helped my lasting back pain
from my spinal fusion after the birth of my second child. The chiropractor was horrified
at what was happening to my neck (cervical spine) with the jaw pulled forward.
Thus, with the appliance in my mouth, he did a high-velocity thrust to my neck.
It felt like the left side of my head collapsed and I was very scared. I never returned.
Instead, I ‘fell apart’.
I had to quit teaching piano. Taking care of two young children was difficult.
My dentist put me in a local dental symposium
for ‘discussion and evaluation’ as I was rapidly deteriorating.
This was my initiation to the MAD (mandibular advancement device).
I became well-known in the Phoenix dental community in the late 70’s.

www.craniofacialteamtexas.com
/craniofacial-conditions-we-treat/facial-fractures

Ken Hub Anatomy | www.kenhub.com/
en/library/anatomy/sacroiliac-joint
My medical history during the 1970’s is a personification of potential repercussions
when there is restriction between the temporal bone and the pelvis.
The Orofacial-Pelvic Connection
1971
Birth of son created paralysis in both legs for four days.
Subsequent scan revealed congenital anomaly at L5-1.
Doctor informed that I could have
more children without issues
1972
Unidentified Intubation injury during a sinus surgery created strange sensation/pain in face.
Injury identified and confirmed
by oral surgeon 26 years later – 1998.
1974 – 1976
1974: Birth of daughter
herniated disc at L5-S1.
1975: Vertebral collapse
after laminectomy
1976: Spinal fusion performed. Prognosis: repeated fusions
until entire spine fused by age 50.
1977 – 78
Dental equilibration
and appliance traumas.
Out of Pain,
Comes Beauty
David Nevue
Non-Conventional Medicine
My medical history from 1981 – 2027
is a confirmation of the amazing potential
of treatment literally
in the ‘hands’ of cranial osteopaths.
Learn how and why the consequences
of a spinal fusion (restriction) in the low back
and a MAD (mandibular advancement device)
on the lower teeth (mandible)
initiated A Perfect Patient Storm
in the world of the Cranial Osteopath.
Fifty years of lasting effects created a medical mystery that has been at long last identified and is slowly and painfully being unraveled:
In late August 2026, my cranial osteopath worked on my mandible, which immediately generated a question from me:
“Is this a result of my jaw having been
pulled forward years ago?”
His eyes lit up as he said
“I have an idea of how to treat the effects
of this mandible being held forward.
Next treatment, we’ll see.”
The following week, after his ‘innovative’ treatment for my mandiblular trauma,
he stated very simply:
“I apologize for taking 30 years
to figure this out.
You now have movement in this area “
Conventional Medicine
My medical history from 1977 – 2027
is a testimonial of what
unsuccessful surgical and medical interventions can create.
Learn how and what the consequences
of a spinal fusion (restriction) in the low back
and a MAD (mandibular advancement device)
on the lower teeth (mandible) can do.
Dentistry and orthopedics had no answers
and created debilitating results in me,
the patient, before thirty-two years of age.
Fifty years of lasting effects created a medical mystery that, at along last, has been identified.
A rare diagnosis of
glossopharyngeal neuroma*,
also known as schwannoma,
an extremely rare benign tumor
with fewer than 50 cases reported worldwide.
Affecting approximately 0.2 to 04 per 100,000 people annually, which translates
to about 2 to 7 cases per million adults.
This diagnosis was made at
The Neurography Institute
by Aaron Filler, MD
(neuroradiolgoist and neurosurgeon),
creator of MR Neurography in 1992.
* When searching for Glossopharyngeal Neuroma, information
frequently turns into Glossopharyngeal Neuralgia.
However, a Glossopharyngeal Neuroma is a structural lesion.
How this evolved over the years is a remarkable story that ventures
‘out of the box’ from conventional medicine.
In the NOW, there appears to be some integration
of the non-conventional (structure and function)
with the conventional (surgery and pharmaceuticals)
– Cranial Osteopathy, Otolaryngology, Neurology, Neurosurgery –
Non-Conventional Medicine
The ‘next treatment’ resulted in release
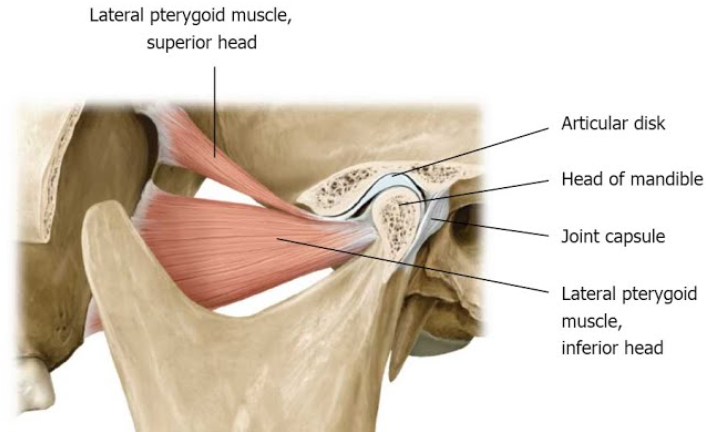
of the medial and lateral pterygoid muscles.
After this, the exceptional happened:
his palpation was able to initiate subtle motion
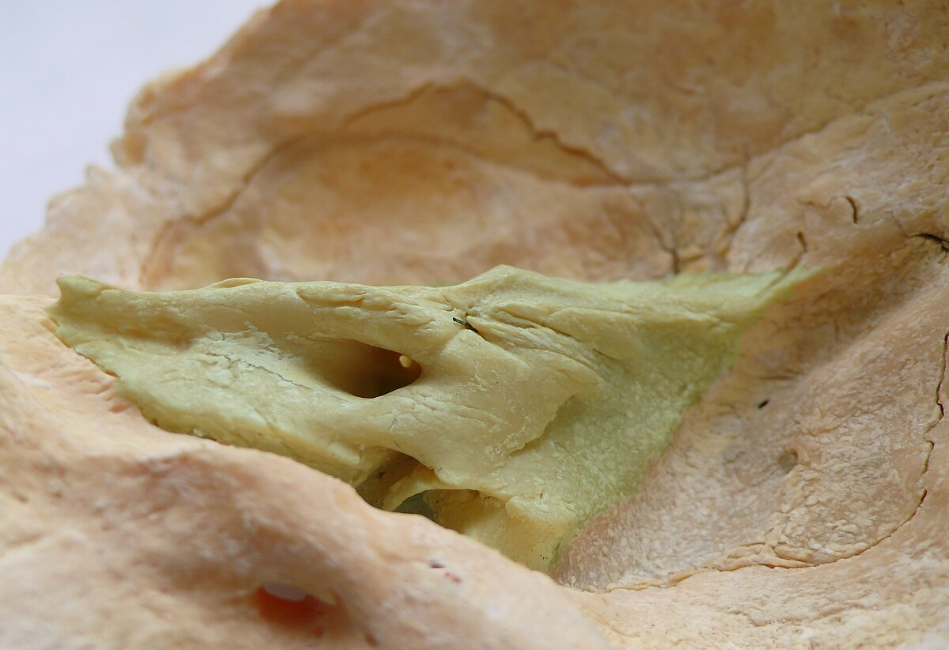
in the petrous portion of the temporal bone
with release of the lateral pterygoid muscle.
He then explained his observation
of my ‘head wobble‘ as motion revolving
around this traumatized, immovable area.
And thus, for the first time, he was able
to initiate normalized motion in this region
My Santa Cruz osteopath has palpated abnormal motion many times, saying: “Carolyn, stop moving your head!” while I am lying on her treatment table. And I state: “I am NOT moving my head!.”
Not only have osteopaths noticed abnormal movement but also dentists and orthodontists have seen the ‘abnormal’. In the mid 80’s
my orthodontist observed:
“The two halves of your palate are like two different people. I need to make two different splints!”
Unstable motion or no motion created
abnormal patterns in the oral cavity.
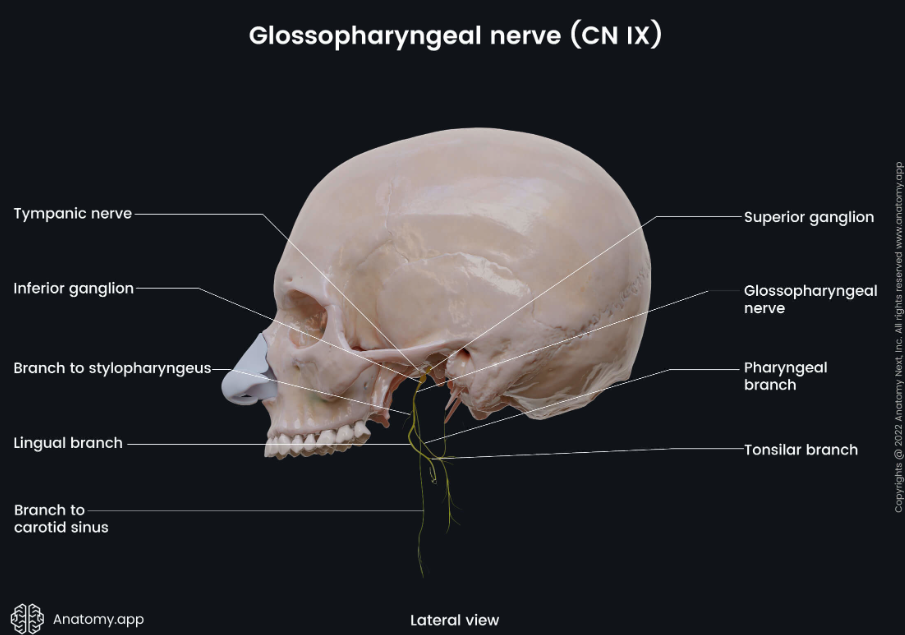
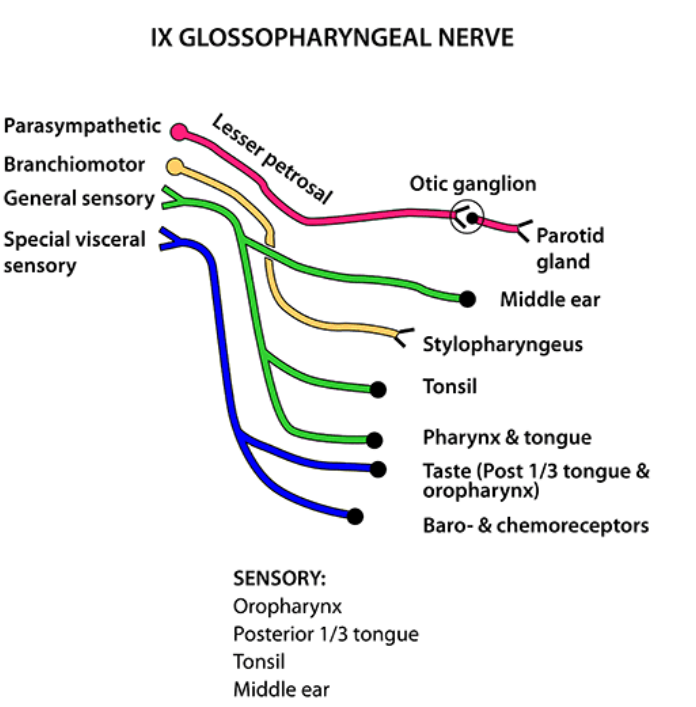
The Petrous Portion of the Temporal Bone
Non-Conventional Medicine
Time will tell how this latest change unravels.
Not only did this monumental change
occur in Phoenix during September,
but also the Santa Cruz osteopathic release
of the sphenoid (April)
as well as the Phoenix release
of the palatine bone (June)
have precipitated significant changes
in sensation and perception.
These three happenings
underscore and substantiate
the traumas that occurred over the years:
Sphenoid
Intubation Injury
Palatine bone
Dropped Palate and Hamular Resection
Pterygoid Process
Mandibular Advancement Appliance with Chiropractic High-Velocity Thrust
Conventional Medicine
It has been one year since the MR Neurography
(Sept 29, 2025) which was suggested by the Phoenix neuroradiologist who read the MRI scan ordered
by my Santa Cruz osteopath.
A good friend of mine has had an acoustic neuroma
for 19 years. She has yearly MRI scans to track
the slow-growth of her neuroma.
I am working with my neurologist to obtain
a comparison read by my Phoenix neuroradiologist, Dr. Lea Alhilali, of her MRI scan with the MR Neurography scan.
I have worked with Dr. Lea Alhilali since 2018,
the creator of Neurology Threads.

My initial reaction has been to return to
The Neurography Institute for a direct comparison
after this first year as well.
What can happen to the glossopharyngeal neuroma and nerve
if there is normalized motion in this area of my skull?
What is the healing potential of a body, even after decades?
NEUROMA
A neuroma is a thickened, swollen mass of nerve tissue
that forms when a nerve is damaged, compressed,
or irritated. Despite sometimes being called a “tumor,”
a neuroma is not cancerous.
It is a disorganized overgrowth of nerve fibers,
connective tissue, and surrounding cellsthat develops
as the body attempts to repair an injured nerve.
FASCIITIS
Fascia is a thin layer of connective tissue that covers
and supports muscles, nerves, blood vessels and organs, providing structural integrity and flexibility.
When this tissue becomes inflamed, irritated, or infected,
it leads to fasciitis, which causes pain, stiffness,
and sometimes tissue damage,
depending on the type and severity
WONDERING
The laryngologist stated that he thought
I had a ‘fasciitis’ in the connective tissue of my throat
…and to keep seeing the osteopaths.
This was during our discussion of the glossopharyngeal neuroma in my throat, when he stated removal
would be surgical malpractice in his book.
This has caused me to wonder how to differentiate
between a ‘neuroma’ and ‘fasciitis’?
Could this be a mass of connective tissue in my throat
as a result of the ‘dropped palate’ and/or laxity in the pterygomandibular raphe ligament?
My Santa Cruz osteopath initially diagnosed
the ‘dropped palate’ and the connective tissue
in my throat as being compromised by the
pterygomandibular raphe (ligament connecting
the maxilla and mandible) affected by this tissue laxity.
.
In 1998, after an oral surgery, a rather large piece
of tonsillar debris snapped out of my mouth.
The word ‘snap’ describes the noise I heard as I simultaneously felt this ‘thing’ in my mouth.
“Oh my gosh, this broke and no one will ever find
the rest of it!” immediately flashed through my mind
as I captured this specimen to send to my oral surgeon
for pathology.
I have revisited the idea that there is ‘something
embedded in my throat’ with many of my doctors.
My ENT informed many times me that a scan would
never be able to show something this small.
I recently found the article;
“Traumatic Neuromas of Peripheral Nerves:
Diagnosis, Management and Future Perspectives”
Frontiers in Neurology | January 2023
And I go there yet again. If a small piece of tonsillar debris was embedded in my throat, I wonder if this could be
the source of a neuroma slowly evolving
around this ‘foreign’ matter.
A Glossopharyngeal Doctor ?
A text message from one of my ENT referrals NOT at AOC Physicians appeared on my phone informing me it was time for my second appointment. I made an appointment, saying that I understood this ENT would probably not treat a glossopharyngeal neuroma but I would like to use him as a sounding board. Within four days, their office called me and told me that the appointment was cancelled since he did not know anything about this issue.
However, later the same week I was able to obtain a referral to a doctor with two specializations:
Oral and Maxillofacial Surgery AND Head and Neck Surgery.
According to this contact, this physician (DMD, MD) would treat a glossopharyngeal neuroma.
Six phone calls to ValleyWise Health and three phone calls to my referring doctor
…and eight days later I have an appointment at the end of September!
What an ordeal to schedule an appointment.
The only nice timing of this ‘delay scenario’: I will have returned from Santa Cruz and
hope to have an ALF appliance in my mouth at this initial appointment with this DMD/head and neck physician!
SCANS
Neurologist, Neurosurgeon
and Neuroradiologist
My ducks are finally lined up in a row.
– I have ordered a second copy of my
2025 MR Neurography scan to take to the initial visit
with the DMD/MD doctor at the end of September.
– My neurologist will contact the neuro-radiologist
Lea Alhilali who initially recommended MR Neurography
and request a comparison read of this initial MRI scan
and the 2025 MR scan. In addition, after my 2026
MR Neurography scan is completed, she will then
have a basis of comparison and hopefully be able
to work with me in Phoenix with MRI scanning.
– I am going to have a conversation about
distinguishing a fasciitis from a neuroma on a scan
with the Santa Moncia neuro-radiologist/neurosurgeon
Aaron Filler.
– I have learned that MR Neurography can image nerve pain much better than MRI….and I hope that because this
is a ‘neuroma’ then MRI can be adequate in the future.
CHANGE
Cranial Osteopath
Since the ‘aha’ moment with my cranial osteopath,
the last three weeks have produced unbelievable change
in not only my mandible and throat but also my entire spine.
I am eagerly awaiting my Santa Cruz Osteopath’s reaction
as well as her response.
Extremes of the good and the bad
…unbelievable pain and then a shift happens.
The shifts are more pronounced and come more quickly.
I have astounding vitality.
As I encounter the momentum of the pain
and breathe into and through the intensity using
Jin Shin Main Central and Supervisor flows with my hands hovering above my body, the shimmering begins
– a ‘shimmering’ similar to the cold laser. I can then relax
into the experience and shift the level of pain.
I know – without any doubt –
that my body is undergoing rapid change.
I am most thankful for my years of this form
of treatment to have not only the strength but also
the courage to walk through the pain that manifests
as change unfolds.
A L F
Advanced Lightwire Functional
ALF appliance
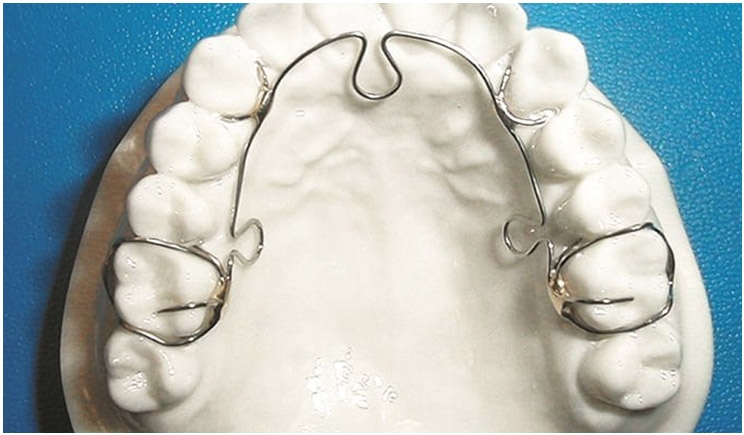
ALF and ARF
Sunday to Wednesday…and I returned home to Phoenix and began teaching
on Thursday and playing Mahjong on Friday with an ALF in my mouth.
Invisible to everyone; however, I certainly could tell it was there!
When I arrived in Santa Cruz, after a two hour plane delay in Phoenix, I was talking on the phone with a friend. When we finished our conversation, I rolled over to charge my phone….and rolled off the bed, landing on my left knee
on a hardwood floor and banging the left side of my head as well! I instantly heard
a voice saying, “Mom!”. Somehow my hand had pressed my son’s phone number and he was there with me on the floor as I tried to get up! So comforting!
The way I dealt with pain was to take the mandibular dental splint
in and out, which would create change…as well as instability.
One of the main purposes of the ALF is to create stability…and it doesn’t come out. The pain has yelled loudly every other day and it’s been very difficult to walk through the pain. Cranial treatment has not relieved the pain; however, I do know there
is monumental change happening as I adapt to a new ‘bite’ (occlusion)
– which feels solid and stable. This is something I have not had in years,
even with the mandibular splint.
And what will my body do with this? It remains to be seen. I saw my Phoenix osteopath on Thursday after returning home on Wednesday evening.
I don’t know if I could have left this in my mouth if I had not received a treatment.
My entire back was reacting not to mention the left side of my throat. I felt like a new person walking out of his office, in spite of the ALF continuing to ‘bark’ loudly
…. ARF, ARF, ARF.

End-of-September Appointments
Cranial Osteopathy and
The Tongue!
Mayo Clinic, Scottsdale
I recently had a second encounter with Mayo Clinic, Scottsdale on the telephone. A diagnosis of glossopharyngeal neuroma is definitely a ‘bad’ word. A surgical ENT was initially recommended by a Scottsdale neurosurgeon who reviewed
my MR Neurography scan.
My neurologist initially referred me
to his Mayo ENT; and four months later, they confirmed they would not make
an appointment for me .
He had used the word ‘glossopharyngeal’ is his referral.
The ENT department refused
to accept me as a patient with this diagnosis.
Last week for whatever reason, I was researching doctors in Phoenix
who would treat a GN neuroma,
and a Mayo clinic ENT’s name appeared. I called and made a ‘telephone’ call back consultation to book an appointment.
And, yet again, Mayo Clinic would NOT deal with this diagnosis at all
and refused to see me.
Valleywise Health
Tomorrow, I have an appointment at Valleywise Health….with a double-degreed physician – a DMD and an MD.
The word glossopharyngeal was used when the appointment was made – a referral from my doctor at Eterna Wellness Clinicwho had called her ENT friend who then referred me
into this facility.
I had been scrambling around getting my information together and vividly remembering the Barrows ENT
who looked straight into my eyes and said ‘you know too much and are misleading your doctors’ and referred me out of Barrows.
I have been anxious about seeing this Valleywise ‘traditional’ doctor because
of my ‘structure/function orientation
in the cranial osteopathic perspective. How to communicate and talk
without being dismissed?
Two worlds of medicine colliding
in an appointment.
All of my ducks were in a row with
a thick pile of medical history and information, CD scans, cold laser and Dr. Turzo’s book ready to accompany me
to my Monday morning appointment.
I sat down to eat and play Mahjong.
And all of a sudden a thought flashed through my ‘anxious’ mind:
“Wow, you are the most amazing patient I’ve ever seen!”
I was so shocked at this flashing through my head, that I started laughing out loud. Something very good had definitely flipped in my psyche.
This stayed with me throughout the evening and went to bed with me.
And I was and will be forever thankful.
Thankful
Michele McLaughlin